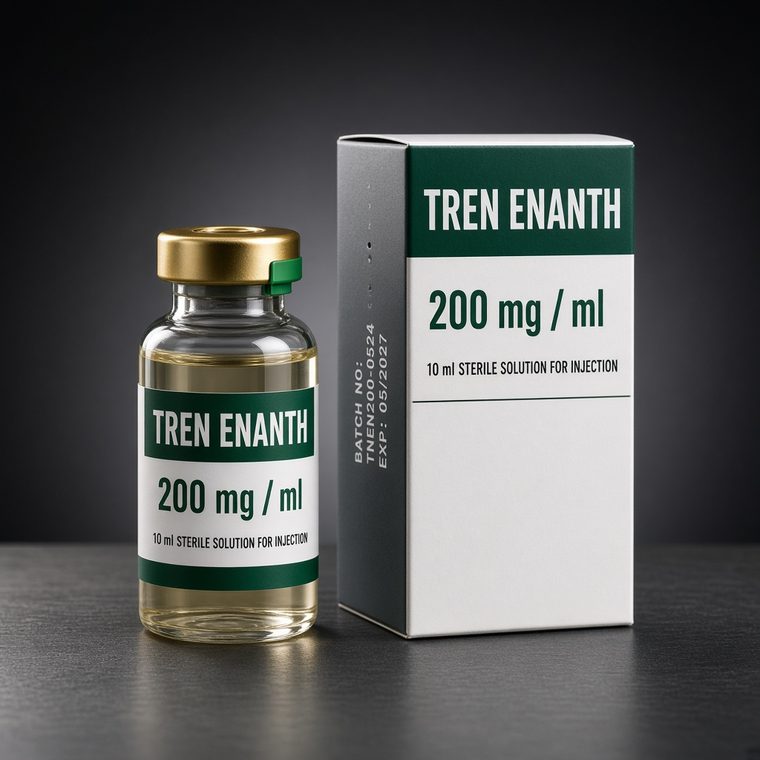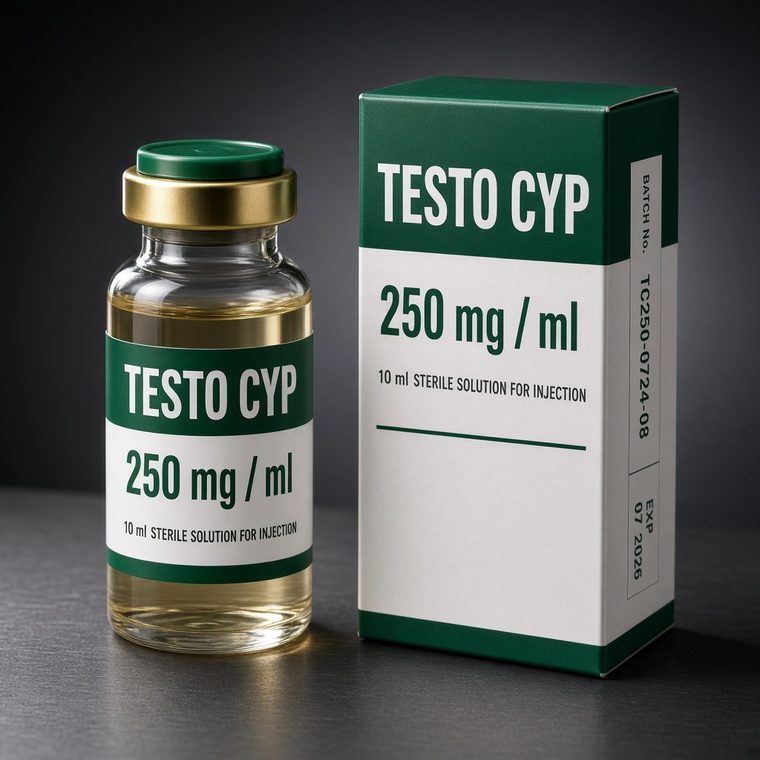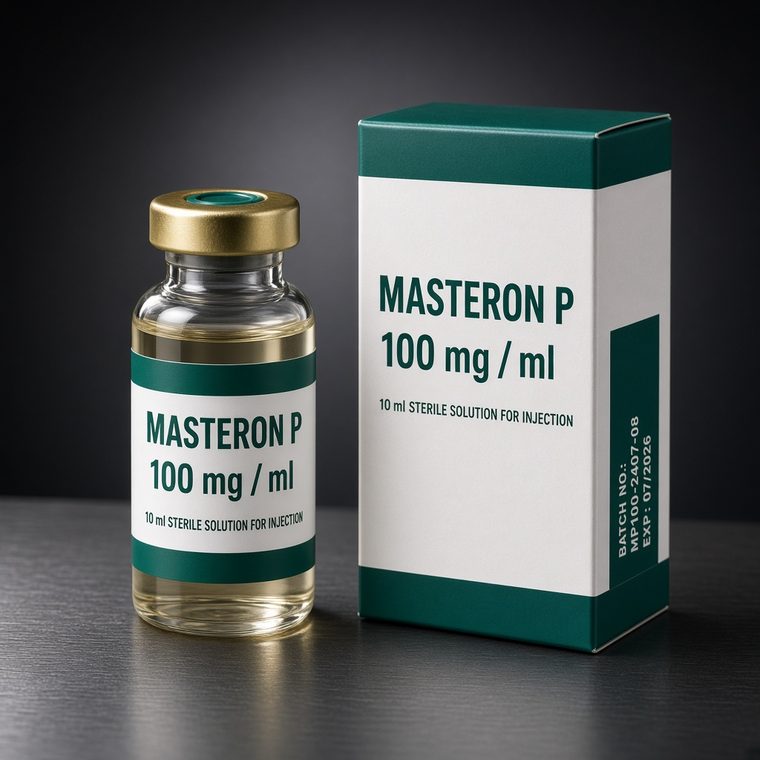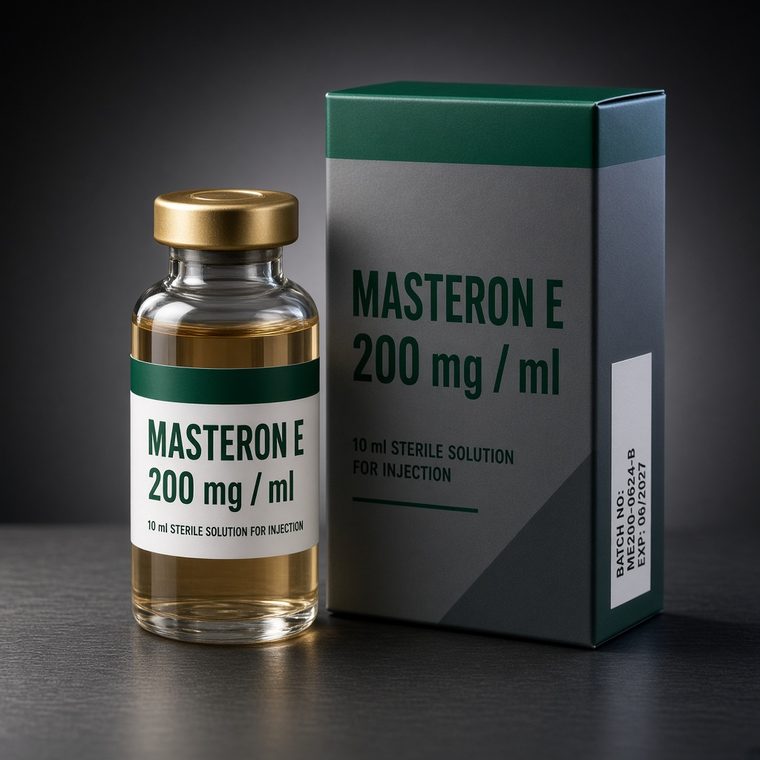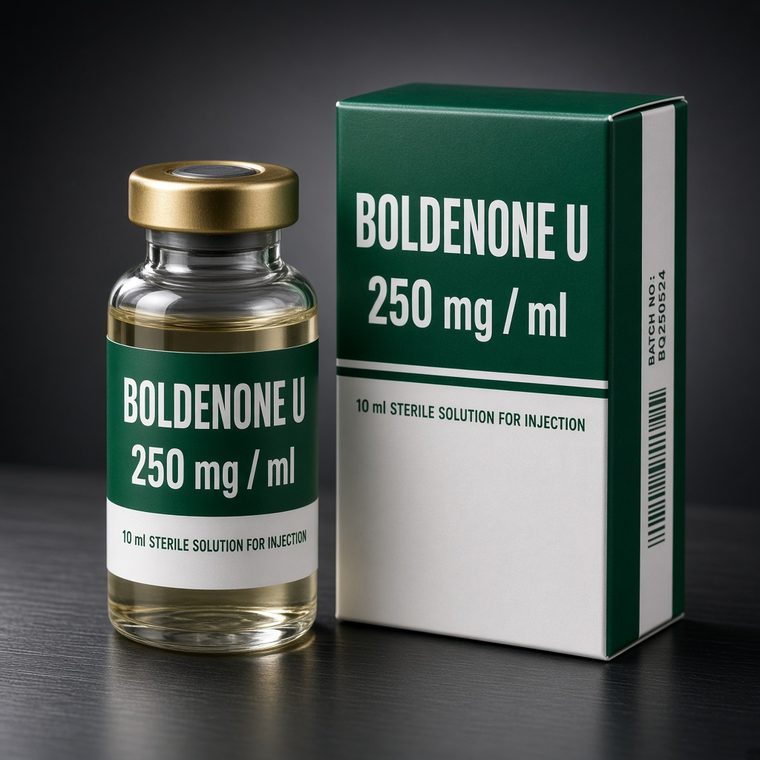
ZPHC / Bioniche Pharma Oil solution
Boldenone Undecylenate (Equipoise) Injections
250 - 300 mg/ml
€48.00
24 verified orders
Dispatch from inside the EU · 3–5 working days to Germany, France, Italy, Spain and Poland
16 compounds in stock
Premium pharmaceutical-grade injectable anabolic compounds. High bioavailability, verified purity with HPLC and Janoshik batch testing.
All items in EU stock, dispatched within 24 h
250 - 300 mg/ml
100 mg/ml 10ml
250 - 400 mg/ml
100 mg/ml
250 mg/ml
150 - 200 mg/ml
250 - 300 mg/ml
250 mg/ml
250 mg/ml
250 - 300 mg/ml
100 mg/ml
200 mg/ml
100 mg/ml
50 mg/ml water-based
The compounds filed under Injectable Steroids are bioactive formulations dissolved in pharmaceutical USP medium-chain triglycerides (MCT) or refined grape seed oil. Injections represent the therapeutic benchmark of sports endocrinology because intramuscular depot absorption avoids the first-pass hepatic toxicity inherent in 17-alpha-alkylated oral tablets.
The foundation of every structured protocol begins with testosterone esters: Testosterone Enanthate for stable twice-weekly administration, Testosterone Propionate for rapid titration, or multi-ester blends such as Sustanon 250 and Supertest 400.
For contest preparation and recomposition, non-aromatising compounds like Trenbolone Enanthate, Masteron, and Primobolan Depot provide dense, dry muscular tissue accumulation with zero subcutaneous water retention.
Esterification at the 17-beta hydroxyl position dictates lipid solubility and release rate from the intramuscular oil depot. As carboxylesterase enzymes progressively cleave the fatty acid chain, free parent hormone enters systemic circulation at a controlled rate governed by the ester half-life.
Once in the bloodstream, molecules diffuse into target skeletal muscle cells, binding cytoplasmic androgen receptors. The activated receptor complex translocates into the cell nucleus, binding Androgen Response Elements (AREs) to stimulate myofibrillar protein synthesis (myosin heavy chains and actin).
Simultaneously, injectables stimulate renal peritubular cells to increase erythropoietin (EPO) output, elevating haematocrit and systemic oxygen delivery to working muscles.
In advanced periodisation, injectable depots are frequently paired with rapid-onset compounds from our Oral Steroids catalogue (such as Dianabol or Anadrol) during the initial 4 to 6 weeks to accelerate immediate glycogen storage and force production.
Because exogenous androgens suppress endogenous hypothalamic-pituitary-gonadal (HPTA) signaling, every cycle requires on-hand aromatase inhibition with Anastrozole (Arimidex), followed by structured recovery through our PCT & Anti-Estrogens protocols.
Review complete administration guidelines in our Beginner Cycle Guide and review aseptic technique in our Steroid Injection Protocol.
Responsible administration mandates laboratory testing: baseline before the cycle, mid-protocol at week 6, and post-recovery. Essential markers include Total & Free Testosterone, Sensitive Estradiol (E2), Complete Blood Count with Haematocrit (< 52%), and a comprehensive metabolic panel covering ALT, AST, and lipid fractions (HDL/LDL).
Post-cycle transition must be planned prior to the first injection. Following ester clearance, SERMs like Tamoxifen Citrate are deployed as documented in our Post-Cycle Therapy Protocol.
All injectables in this catalogue originate from licensed GMP facilities: ZPHC, Pharmacom Labs, Bioniche Pharma, and Hilma Biocare.
Every vial features an anti-counterfeit security hologram with a scratch-off serial verifiable at source. Orders ship in plain, shock-absorbent packaging from inside the Schengen zone with 3 to 5 day transit across Europe.
Reference material compiled from published pharmacological literature. Not medical advice. Obtain baseline bloodwork and speak to a physician before starting any protocol.