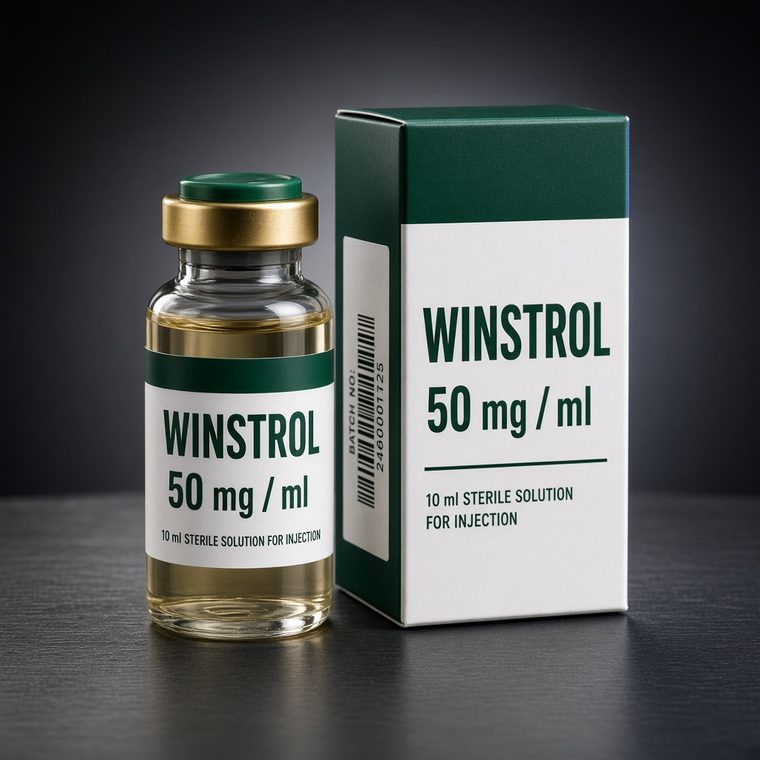
Winstrol Suspension (Injectable Stanozolol): a pharmacological reference
Oral anabolic-androgenic pharmacology represents a specialized class of chemical formulations designed to overcome the primary hepatic first-pass metabolism that typically inactivates oral steroidal compounds. By incorporating a 17-alpha alkylation (typically a methyl or ethyl group at carbon-17), these molecules survive digestive and liver clearance, reaching systemic circulation intact.
Chemistry and classification
This direct oral bioavailability produces immediate pharmacokinetic saturation, initiating cellular protein synthesis within hours of ingestion. Compounds in this category range from powerful water-retaining mass catalysts like Anapolon (Oxymetholone) and Dianabol to razor-sharp contest conditioning and explosive strength agents such as Anavar (Oxandrolone), Winstrol (Stanozolol), and Halotestin.
Due to their potent impact on hepatic metabolism and serum lipid profiles, oral formulations are structured as tactical 4 to 8 week protocol accelerators, deployed either at the inception of a cycle (kickstarter) or during pre-contest preparation to achieve peak muscle density and vascularity.
Clinical history
The development of 17aa oral pharmacology accelerated through the late 1950s and 1960s in response to clinical demands for needle-free therapeutic administration. Legendary figures such as Dr. John Bosley Ziegler synthesized Dianabol in 1958 in collaboration with Ciba to counter Soviet athletic dominance.
Concurrently, Searle laboratories engineered Oxandrolone (Anavar) in 1964 with an oxygen atom replacing carbon-2, creating a compound with profound anabolic activity and exceptionally low pediatric and female toxicity, approved for recovering trauma victims, severe burns, and post-surgery cachexia.
Throughout modern sports history, oral anabolics have remained foundational tools across sprinting, Olympic weightlifting, and competitive bodybuilding for their rapid strength augmentation and non-esterified pharmacokinetic speed.
Mechanism of action
Upon gastrointestinal absorption, the active compound enters the portal circulation and transits hepatic tissue without significant molecular degradation due to the steric hindrance provided by the 17-alpha methyl group.
Once in peripheral circulation, the molecule binds with high affinity to target tissue Androgen Receptors. In the case of Stanozolol and Proviron, an additional profound mechanism is their intense affinity for Sex Hormone-Binding Globulin (SHBG). By fiercely binding to SHBG, they displace bound testosterone, dramatically multiplying the biologically active "free" testosterone fraction in circulation.
Anavar uniquely stimulates intracellular phosphocreatine (PCr) synthesis within muscle cells, dramatically accelerating ATP resynthesis during maximal resistance sets without water weight gain or aromatization.
Anapolon and Dianabol induce massive non-genomic cellular glycogen swelling and fluid retention within the myofibrillar matrix, maximizing mechanical leverage across tendons and skeletal joints.
Pharmacokinetics
Oral anabolics possess rapid biological half-lives ranging from 4 to 6 hours (Dianabol), 8 to 9 hours (Winstrol, Turinabol), to 9 to 12 hours (Anavar). Proviron exhibits an elimination half-life of 12 hours.
Due to these compressed half-lives, daily doses are divided into two or three administrations spaced evenly throughout the day to avoid serum peak-and-trough turbulence and sustain constant androgen receptor saturation.
Metabolized by cytochrome P450 enzymes and excreted primarily through renal filtration, urinary detection windows range from 3 to 4 weeks (Anavar, Dianabol) up to 2 months (Winstrol, Turinabol).
Use in sport
Athletic deployment is strictly goal-specific: Dianabol and Anadrol are deployed during heavy off-season mass phases where rapid bodyweight accumulation, maximum mechanical leverage, and supreme joint lubrication are needed.
Conversely, Anavar, Winstrol, and Turinabol are the premier choices for weight-class-restricted athletes, powerlifters, and bodybuilders seeking dry, dense, striate musculature, explosive speed, and enhanced recovery without water weight or bloat.
Halotestin stands alone as a psychological and central nervous system amplifier, utilized in the final 2 weeks before powerlifting meets or combat sports bouts to ignite aggression, neuromuscular drive, and rock-hard density.
Bloodwork and monitoring
Given 17aa hepatic passage, comprehensive biomarker surveillance must prioritize liver function enzymes: Alanine Aminotransferase (ALT), Aspartate Aminotransferase (AST), Alkaline Phosphatase (ALP), Gamma-Glutamyl Transferase (GGT), and Total Bilirubin.
Equally critical is lipid fractionation: oral anabolics stimulate hepatic lipase, which actively catabolizes High-Density Lipoprotein (HDL) while elevating Low-Density Lipoprotein (LDL). Baseline and mid-cycle lipid panels are imperative.
Supportive supplementation with proven hepatoprotective agents (TUDCA at 500-1000 mg/day, NAC at 1200 mg/day, and Citrus Bergamot for lipids) is standard practice.
Reference Protocol
For complete reference ranges, marker intervals, and clinical harm reduction steps, see our documentation:
First Steroid Cycle Guide for Beginners: Protocols, Bloodwork & Safety →Adverse effects and harm reduction
Hepatic stress: Elevation of transaminase enzymes is universal with 17aa compounds, requiring strict adherence to conservative 4 to 8 week cycle limits and complete avoidance of alcohol or hepatotoxic medications.
Lipid dyslipidemia: Marked drops in protective HDL cholesterol require dietary incorporation of omega-3 fatty acids, soluble fiber, and cardiovascular exercise.
Androgenic side effects (acne, androgenetic alopecia) depend on the specific compound: Anavar is exceptionally mild, whereas Winstrol and Halotestin are strongly androgenic in susceptible scalp follicles.
Purity and authentication
All oral pharmaceutical tablets supplied through Muscle-Shop.eu are manufactured under GMP cleanroom conditions utilizing micro-crystallized active ingredients for uniform tableting dispersion and rapid gastrointestinal dissolution.
HPLC laboratory batch assays guarantee precise milligram content per tablet (e.g. 10 mg Oxandrolone, 50 mg Oxymetholone, 10 mg Stanozolol) within +/- 1.5% analytical tolerance.
Blister packaging with pharmaceutical foil backing protects hygroscopic tablets from environmental moisture, ensuring indefinite stability and complete potency.
Common questions
- Can an oral-only cycle be safely performed?
- Oral-only cycles without a Testosterone base are strongly discouraged. 17aa oral steroids suppress endogenous testosterone production within weeks. Without testosterone to provide background estrogen, users experience severe joint pain, loss of libido, lethargy, and cardiovascular strain. Always use at least a low TRT-dose testosterone base.
- How can liver stress be minimized while using oral anabolics?
- Limit oral cycles to a strict maximum of 6 to 8 weeks, incorporate clinically proven liver protectors such as TUDCA (500-750 mg daily) and N-Acetyl Cysteine (NAC 1200 mg daily), drink at least 3-4 liters of water daily, and avoid alcohol completely.
- What makes Anavar (Oxandrolone) uniquely popular among female athletes?
- Oxandrolone has an exceptionally low androgenic rating of 24 compared to its high anabolic score of 322-630. In conservative dosages (5-10 mg daily), it provides clean muscle preservation and fat loss with an extremely low risk of virilization side effects.
This page is reference material compiled from published pharmacological literature. It is not medical advice and does not describe a prescription. Discuss any compound with a physician and obtain baseline bloodwork before use.